October 15, 2026
Emergency Dentist Care After a Sports-Related Dental Injury
By @archerkoyo674

A dental injury during sports has a way of changing the pace of a day in an instant. One moment, a child is running onto a soccer field or an adult is leaning into a rebound under the basket. The next, there is blood in the mouth, a broken front tooth in a hand, or a tooth that is suddenly loose and painful. It is dramatic, messy, and often frightening, especially because injuries to the teeth and mouth tend to look worse than they are, while sometimes hiding serious damage beneath the surface.
This is where timely emergency dental care matters. A sports-related dental injury is not just a cosmetic problem. Depending on the force, the tooth may be cracked below the gumline, displaced in the socket, pushed into the bone, or fully knocked out. The lips, cheeks, tongue, jaw joints, and surrounding bone can also be affected. Quick decisions in the first 30 to 60 minutes can influence whether a tooth can be saved, how much treatment will be needed later, and how comfortable the recovery will be.
People often assume that a dental emergency belongs in the emergency room. Sometimes it does, especially when there is heavy bleeding, trouble breathing, loss of consciousness, suspected jaw fracture, or significant facial trauma. But when the injury centers on the teeth, gums, and supporting structures, an Emergency Dentist is usually the clinician best equipped to assess and treat it promptly. In many cases, seeing the right dental professional quickly can mean the difference between preserving the natural tooth and losing it.
What counts as a sports-related dental emergency
Not every hit to the mouth produces a true emergency, but many do. The challenge is that athletes, coaches, and parents often underestimate dental trauma if the person can still speak, drink water, or get back on their feet. Teeth do not always give immediate, obvious signals. A small chip might be mostly cosmetic, while a tooth that looks only slightly displaced may have suffered a significant ligament injury.
The cases that deserve same-day evaluation usually include a knocked-out permanent tooth, a tooth that has moved out of position, a loose tooth after impact, a deep fracture, persistent bleeding from the gums or lips, pain when biting, or swelling that begins to build after a blow. Even when pain is mild, a change in bite can be a warning sign. If the teeth no longer meet normally, something may be out of alignment.
Children present a special wrinkle because they may injure either primary teeth, permanent teeth, or both depending on age. A baby tooth that is knocked out is handled differently from a permanent tooth. Reimplanting a primary tooth is generally not recommended because of the risk to the developing adult tooth underneath. That is one of the most common points of confusion on the sidelines.
The injuries dentists see most often after sports impact
Different sports produce different patterns of trauma. Basketball and soccer often lead to elbow, shoulder, or head collisions. Baseball, hockey, lacrosse, and cricket add high-speed projectiles. Martial arts, skateboarding, cycling, and gymnastics bring falls and blunt impact. Across those settings, several injuries show up again and again.
- Chipped or fractured teeth, ranging from a small enamel chip to a deep crack involving the nerve.
- Luxation injuries, where the tooth is loosened, pushed sideways, driven deeper into the socket, or partially pulled out.
- Avulsion, which means the tooth has been completely knocked out.
- Soft tissue injuries to the lips, cheeks, tongue, or gums, sometimes with tooth fragments embedded in the tissue.
- Jaw soreness or bite changes that may indicate joint injury or a facial bone fracture.
Each of these injuries has its own urgency and treatment path. A chipped edge on a front tooth may be repaired with bonding if the nerve is not involved. A tooth that has been displaced often needs repositioning and splinting. A knocked-out permanent tooth is a true time-sensitive emergency. Soft tissue lacerations may need cleaning, sutures, or imaging if a fragment is missing.
The first few minutes matter more than most people realize
The mouth is a forgiving place in some respects. It has an excellent blood supply, and many soft tissue injuries heal quickly. Teeth are less forgiving. The periodontal ligament, the delicate tissue fibers that anchor a tooth to the socket, begins to suffer once a tooth is out of the mouth or heavily displaced. That is why immediate handling is so important.
A permanent tooth that is knocked out has the best chance of successful reimplantation if it is returned to the socket quickly or stored correctly and seen by an Emergency Dentist without delay. The often-quoted ideal window is within 30 minutes, but teeth can sometimes still be saved after that depending on storage conditions and the nature of the injury. Every minute still matters.
The same principle applies to fractures and displaced teeth. The longer a damaged tooth remains untreated, the greater the chance of bacterial contamination, swelling, pulp injury, or complications with the bite. Pain often intensifies later, once adrenaline wears off and inflammation builds.
What to do right away on the field, court, or sideline
People tend to panic when there is blood involved, and mouth injuries bleed easily. A calm, simple response is better than improvisation. The immediate goal is to control bleeding, protect the tooth and surrounding tissues, and arrange prompt professional care.
- Check for bigger red flags first, such as loss of consciousness, vomiting, confusion, breathing problems, or suspected jaw fracture. If any are present, seek emergency medical help immediately.
- If a permanent tooth is knocked out, pick it up by the crown, not the root. If it is dirty, rinse it briefly with milk or saline, or clean water for only a few seconds if nothing else is available.
- If possible, place the tooth back into the socket gently and have the person bite softly on gauze. If that cannot be done, store it in milk, saline, or inside the cheek if the person is old enough not to swallow it.
- Control bleeding with clean gauze or cloth and apply a cold compress to the outside of the mouth or face.
- Contact an Emergency Dentist at once and describe the injury clearly so the office can prepare for urgent treatment.
A few common mistakes deserve mention because they happen often. Do not scrub the root of a knocked-out tooth. Do not wrap it in dry tissue. Do not store it in plain tap water for long if better options are available. Do not attempt to force a displaced tooth aggressively back into place if you are unsure of the position. And do not assume a small fracture can wait for weeks just because the athlete is not crying.
Why the type of tooth changes the plan
One of the biggest practical distinctions in sports injuries is whether the damaged tooth is primary or permanent. For a seven-year-old, that can be surprisingly difficult to tell in the front of the mouth, where the transition from baby teeth to adult teeth is still underway.
If a permanent tooth is knocked out, immediate reimplantation is usually the goal. If a primary tooth is knocked out, the focus is different. The dentist will manage pain, protect the area, and monitor the developing permanent tooth. Reimplanting a baby tooth can injure the underlying successor tooth and is generally avoided.
Loose or pushed-in primary teeth also require professional evaluation, even when the long-term plan is observation. A displaced baby tooth can interfere with bite, lacerate soft tissue, or affect the erupting permanent tooth. Parents sometimes feel relieved when they hear, “It is only a baby tooth,” but that phrase can be misleading. A primary tooth injury still deserves attention.
What an Emergency Dentist will evaluate
When patients arrive after a sports injury, the exam is about much more than the visible broken edge. An experienced Emergency Dentist checks how the teeth fit together, whether any teeth are mobile, whether there is tenderness to percussion, where the gums are torn, and whether the lips or cheeks may contain embedded fragments. The dentist also looks for signs that the injury extends beyond the teeth into the alveolar bone or jaw.
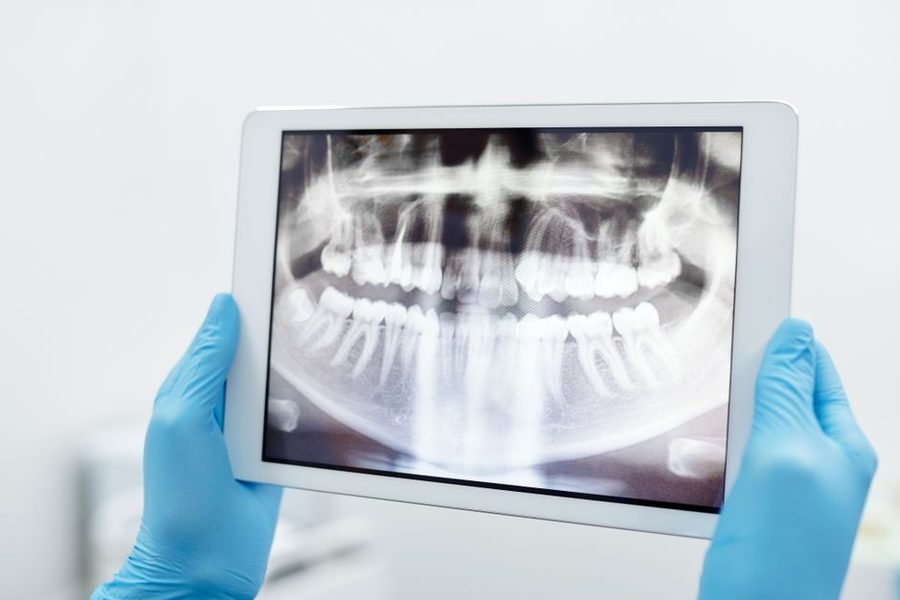
X-rays are frequently part of the visit, though the exact imaging depends on the case. Sometimes a standard dental radiograph is enough. In more complex trauma, additional views help reveal root fractures, intrusion, socket damage, or hidden tooth fragments in soft tissue. If jaw fracture is suspected, hospital-based imaging may be needed.
Pulp testing may be attempted, but it is not always reliable immediately after trauma. A tooth can test “sleepy” or nonresponsive in the first hours or days and still recover. This is one reason follow-up matters. Trauma care is rarely one-and-done. It often involves monitoring over weeks or months to see whether the nerve survives, whether root resorption develops, and whether the tooth remains stable.
Treatment depends on force, timing, and tooth maturity
Sports injuries are not treated by a one-size-fits-all formula. Two patients may both say, “I got hit in the mouth,” while needing entirely different care. The age of the patient, the stage of root development, the time since injury, the amount of contamination, and the direction of the force all influence the decision.
A minor enamel chip may need polishing or bonding. A fracture that exposes dentin, the inner yellow layer, should be sealed relatively quickly to reduce sensitivity and bacterial penetration. If the fracture exposes the pulp, the treatment may involve a pulp cap, pulpotomy, or root canal, depending on the age of the tooth and the extent of the injury.
A displaced tooth often needs local anesthesia, gentle repositioning, and a flexible splint for a short period. A tooth that has been driven deeper into the socket, called intrusion, is more complicated. In a child or teenager with an immature permanent tooth, the dentist may watch for spontaneous reeruption in select cases. In other situations, surgical or orthodontic repositioning may be required.
Knocked-out teeth are among the most urgent and nuanced cases. Reimplantation may be followed by splinting, antibiotics in some cases, tetanus review through the patient’s physician if the wound is contaminated, and later root canal treatment depending on the tooth’s maturity and extraoral time. Saving the tooth is the priority, but the long-term outcome can vary. Some replanted teeth do well for years. Others eventually undergo root resorption or ankylosis despite proper care. That does not make reimplantation a mistake. Particularly in younger patients, even temporary retention of the natural tooth can preserve bone and buy valuable time during growth.
The pain question, and why “it doesn’t hurt much” can be misleading
Pain after dental trauma is unpredictable. A cracked tooth can ache intensely with air or cold. A displaced tooth may feel dull and heavy rather than sharply painful. A knocked-out tooth, oddly enough, may produce more shock than pain at first. Soft tissue injuries sting and bleed, but sometimes distract from deeper structural damage.
Patients often downplay symptoms because they want to keep playing, finish the tournament, or avoid disappointing teammates. Adults do it too, not just teenagers. I have seen cases where someone finished a game with a loose front tooth and sought care only the next day when the bite felt “off.” By then, the tooth had dried out, swollen around the socket, and required more extensive stabilization than it might have needed earlier.
That is one reason coaches and athletic trainers should treat any visible dental change seriously. If a tooth looks shorter, longer, rotated, or pushed back, it is not a cosmetic issue to postpone casually. Even mild movement can indicate ligament and bone injury.
Soft tissue wounds can hide more than blood
A split lip or cut cheek often grabs attention first, and rightly so. But when a tooth fractures on impact, small pieces can end up lodged in the lip or mucosa. If a fragment is unaccounted for, the dentist may order imaging of the soft tissue to make sure nothing is embedded. Leaving a fragment behind can lead to persistent swelling, tenderness, or delayed healing.
Cleaning and irrigation are important, especially when the injury happened on a field, court, or trail. Dirt, turf particles, or debris can contaminate the wound. Some lacerations need sutures, but not all do. The decision depends on depth, location, wound edges, and whether the tissue will approximate well on its own.
There is also the matter of scarring. Inside the mouth, healing is usually favorable. The lips are less forgiving, particularly near the border where the pink and skin meet. If a lip laceration crosses that boundary or is gaping significantly, timely treatment becomes more important for both function and appearance.
Follow-up is part of trauma care, not an optional extra
This is where many patients are caught off guard. They come in for emergency treatment, get the tooth stabilized or restored, and assume the matter is settled. Often it is only partly settled.
Traumatized teeth need observation because complications can emerge gradually. The pulp may die weeks later. Root resorption can begin quietly. A tooth that seemed stable can darken or become sensitive. In children and adolescents, the effects of trauma may interact with ongoing growth and eruption patterns. For that reason, emergency treatment is usually followed by scheduled reviews, repeat x-rays, and vitality checks.
The timeline varies, but it often extends over several months and sometimes longer. That is not alarmist. It is standard good care. The purpose is to catch trouble early, when intervention is simpler and outcomes are better.
When hospital care is the better first stop
Although an Emergency Dentist is often the right first call, some sports injuries clearly belong in medical emergency care first. If the athlete has lost consciousness, has memory changes, severe headache, nausea, unequal pupils, or other signs of head injury, dental concerns become secondary to neurological evaluation. The same applies to uncontrolled bleeding, difficulty breathing, obvious facial fracture, or inability to open and close the jaw normally after major trauma.
There are also blended situations. A cyclist may arrive with a knocked-out tooth, chin laceration, and suspected broken jaw. That person may need emergency medical assessment first, followed by dental treatment once medically stable. Good trauma care depends on triage, not territorial thinking. The goal is not to decide whether the problem is “medical” or “dental.” The goal is to address the most urgent risks in the right order.
Recovery at home after emergency treatment
Once the immediate treatment is done, the next several days matter. The mouth is active all the time. We talk, chew, swallow, clench, and sleep in ways that can irritate an injured area. Patients generally do better when they understand how protective the early healing window needs to be.
A soft diet is often advised for several days, sometimes longer if the tooth has been splinted. That means avoiding crusty bread, hard pizza edges, nuts, ice, jerky, raw carrots, and similar foods that require forceful biting. Good oral hygiene remains essential, but it needs to be gentle around the injured site. Rinses may be recommended, depending on the injury and treatment.
Pain control is usually manageable with common https://www.behance.net/smyledbakersf anti-inflammatory medication if medically appropriate, though some injuries require more tailored planning. Swelling tends to peak in the first day or two. Persistent increasing swelling, fever, a bad taste, worsening pain, or new mobility should prompt a call back to the dentist.
For athletes, the hardest part is often returning to play. The answer depends on the injury. A simple bonded chip may allow quick return once comfort permits. A replanted or splinted tooth, or a case involving jaw injury, typically requires more caution. A well-fitted mouthguard becomes even more important after trauma.
Mouthguards, and why “I don’t like how it feels” is not a small issue
Prevention deserves a candid look because many sports-related dental injuries are at least partly preventable. Mouthguards reduce the risk of broken teeth, soft tissue cuts, and some jaw impact injuries. But their effectiveness depends heavily on fit and actual use.
Store-bought boil-and-bite guards are better than nothing, but they vary widely. Some are bulky, affect speech, or make athletes feel as if they cannot breathe comfortably, especially during high-intensity play. When that happens, compliance drops. The guard spends more time in a bag than in the mouth.
Custom mouthguards from a dentist cost more upfront, but for athletes in contact or collision sports, they are often worth it. They fit better, interfere less with breathing and communication, and can be designed around orthodontic appliances or prior dental work. For a teenager in braces or an adult with veneers on the front teeth, those details matter. A cheap guard that is never worn offers no protection. A comfortable guard used consistently changes the odds.
The psychological side of a front tooth injury
Not every consequence is physical. A broken or missing front tooth can hit confidence hard, especially in teenagers and young adults. Some patients become self-conscious about smiling, speaking, or returning to school or work. Even a temporary repair can make a large emotional difference.
That is one reason dentists often try, when clinically reasonable, to provide an aesthetic interim solution early. Repositioning, bonding, smoothing rough edges, or replacing visible missing structure, even provisionally, can help a patient feel like themselves again. In sports dentistry, restoring function matters, but so does restoring normalcy.
Choosing the right emergency dental response
When calling an Emergency Dentist after a sports injury, clear communication helps speed the process. The office will want to know when the injury happened, whether the tooth is knocked out or just broken, whether there is swelling or bleeding, whether the patient is a child or adult, and whether the tooth is currently in milk, back in the socket, or dry. Those details are not administrative trivia. They shape preparation and urgency.
A practice that regularly handles trauma will know how to triage quickly and give practical instructions before arrival. That can include storage advice for an avulsed tooth, instructions about bringing broken fragments, or direction to seek hospital care first if signs point to concussion or fracture.
Sports-related dental injuries are unsettling, but they are manageable when handled promptly and intelligently. The athlete does not need perfection in the first minute. They need calm first aid, sensible triage, and fast access to skilled dental care. That combination saves teeth, limits complications, and shortens the road back to normal eating, speaking, and playing.
Smyle Dental Bakersfield
2016 E St, Bakersfield, CA 93301, United States
+16614939040
FAQ About Emergency Dentist
What counts as a dental emergency?
Severe tooth pain, facial swelling, uncontrolled bleeding, a knocked-out or displaced tooth, and significant dental trauma may need prompt assessment. Trouble breathing or rapidly increasing swelling requires urgent medical help.
What should I do if a permanent tooth is knocked out?
Handle the tooth by the crown rather than the root, keep it moist, and contact a dentist immediately. Fast treatment can improve the chance of saving the tooth.
Can an emergency dentist treat severe tooth pain the same day?
Same-day care may be available depending on the cause and schedule. The dentist will examine the area, may take digital X-rays, and recommend treatment based on the diagnosis.
Should I go to the emergency room for dental swelling?
Seek urgent medical care for trouble breathing, difficulty swallowing, rapidly spreading facial swelling, or other severe symptoms. A dentist can assess the underlying dental cause and provide appropriate follow-up care.
❧